
Actinic Keratosis
Actinic keratosis dermoscopy
Actinic keratosis is an irregular, skin coloured, red or pigmented papule or plaque and is most often found on a bald scalp, ear, face or back of the hand. Multiple lesions are often present. Other features may include:
- A white or yellow, scaly, warty or horny surface
- Tenderness.
Nonpigmented actinic keratosis on the face
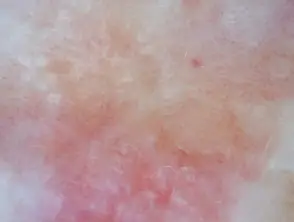
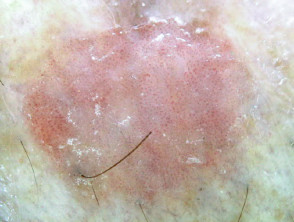
Nonpigmented actinic keratosis on the face is characterised by a ‘strawberry pattern’ on dermoscopy. The border of the lesion is often well demarcated but may merge into surrounding skin as many patients have extensive sun damage. Other features may include:
- A pink, structureless background
- A pink to red pseudonetwork created by straight or wavy vessels surrounding the hair follicles
- Prominent small skin coloured, white or yellowish spots corresponding to follicular openings of variable size.
- Skin coloured or white circles around a yellowish clod (this is a keratotic plug)
- Four dot clods (rosettes) under polarised light
- Surface scale.
Nonpigmented actinic keratosis on nonfacial skin
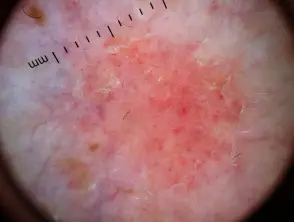
Actinic keratosis on nonfacial skin usually exhibits a nonspecific pattern. Features may include:
- Irregular shape
- Surface scale (white or yellow).
- Sometimes, oyster shell-like concentric yellow structures
- Erythema, sometimes with dotted vessels (tiny crops of red dots)
- Rosettes (polarised light only)
- Short shiny streaks.
Dermoscopic features of pigmented actinic keratosis
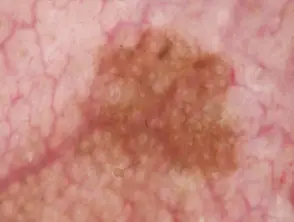
Pigmented actinic keratosis has a similar appearance to nonpigmented actinic keratosis with the addition of pigmented structures. The most common dermoscopic findings are:
Other features include:
- Hyperpigmented follicular openings
- Brown structureless areas
- Annular–granular structures.
Other features include:
- Brown background skin
- Angulated superficial brown lines
- Perifollicular inner grey halo
- Sometimes, grey rhomboidal structures: grey confluent dots arranged in lines or grey-to-brown linear structures located between follicular structures.
What is the dermoscopic differential diagnosis of actinic keratosis?
Actinic keratosis is diagnosed by a combination of clinical and dermoscopic features and sometimes can be difficult to distinguish from other lesions. It may coexist with solar lentigo, cutaneous squamous cell carcinoma, and lentigo maligna.
Cutaneous squamous cell carcinoma
Cutaneous squamous cell carcinoma can arise from actinic keratosis. Differentiation is determined by dermoscopic findings of peripheral white around a central scaly core (the original actinic keratosis).
Squamous cell carcinoma in situ
Dotted/coiled vessels tend to be scattered more randomly in actinic keratosis than in intraepidermal carcinoma where they are arranged in lines or clusters. Vascular structures in squamous cell carcinoma in situ show greater variation in size and structure.
Lentigo maligna
The following four features are significantly associated with lentigo maligna: hyperpigmented follicular openings, obliterated follicular openings, annular-granular structures, and pigmented rhomboids.
Pigmented rhomboids and obliterated follicular openings are significantly more frequent in lentigo maligna than pigmented actinic keratosis.
Lentigo maligna tends to be smooth to the touch, whilst actinic keratosis tends to be rough in texture. The border of lentigo maligna has variable abruptness (fading in some areas, sharp in others) whereas pigmented actinic keratosis tends to have a defined border. Lentigo maligna may have asymmetrical pigmented follicular openings and a darker dot located within ostial openings (a concentric circle or the isobar sign); a finding rarely seen in pigmented actinic keratosis.
Psoriasis
Psoriasis presents with red scaly plaques. Occasionally a solitary plaque of psoriasis may be confused with actinic keratosis. It has a regular structure. The uniform scale tends to be whiter and more silvery in psoriasis compared to the irregular yellowish scale of actinic keratosis. Dotted blood vessels are distributed uniformly throughout the lesion in psoriasis.
What is the histological explanation for the dermoscopic findings in actinic keratosis?
The correlation between histological and dermoscopic features of actinic keratosis is poor.
Rosettes
The exact histological explanation of rosettes is unclear but they are thought to be due to an interaction between polarised light and narrowed keratin-filled, or fibrotic adnexal openings. Haspeslagh et al found that small rosettes (0.1–0.2 mm) corresponded to concentric horny material in follicular and eccrine ducts at the infundibular level and larger rosettes (0.3–0.5 mm) to perifollicular concentric fibrosis.
Surface scale
Alternating orthokeratosis and parakeratosis.
Strawberry pattern
Vessels between hair follicles, with white haloed follicular openings.
Circles
Circles that appear in pigmented keratosis are due to the involvement of follicular infundibula.
Frequently asked questions
This will be dependent upon the location of the area of the cancer/lesions.
The type of anaesthesia will be determined by the size and location of the area to be treated and could be either local anaesthesia, twilight sedation or general anaesthesia.
With any surgical procedure, there are risks involved and most problems are easily treated and settle with time.
General risks of any surgery include excessive bleeding, reaction to any of the medications (including anaesthesia), infection, poor healing or excessive scarring.
Concerned about a spot on your skin?
Book a skin check with one of our doctors by calling us on (02) 7500 5858 or book online.